
PRP for Hip Osteoarthritis: Evidence, Candidates, and Recovery
PRP may help selected patients manage hip osteoarthritis symptoms, but diagnosis, image guidance, rehabilitation, and realistic expectations determine whether it is a reasonable option.
Understanding hip osteoarthritis
Hip osteoarthritis develops when the joint’s cartilage and other tissues change over time, producing pain, stiffness, and reduced function. Symptoms often include groin pain, discomfort with walking or stairs, loss of rotation, difficulty putting on shoes, and reduced tolerance for exercise. Imaging may show arthritis, but the image alone does not prove that the hip joint is the only source of pain.
Pain around the hip can also come from tendons, the lower back, bursae, or other structures. A careful history, examination, and review of imaging help determine whether an intra-articular treatment makes sense. The first question is not simply whether PRP can be injected; it is whether the joint is the right target.
Conservative treatment may include activity modification, strength and mobility work, weight management when relevant, medication, and selected injections. Surgery can be appropriate for advanced disease with major functional limitation. PRP is considered in the space between basic conservative care and surgery for some patients.
How PRP is used for the hip
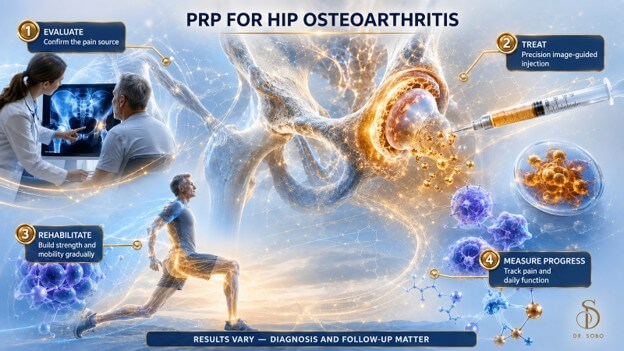
A blood sample is processed to concentrate platelets, and the prepared product is injected into the hip joint. Because the hip is deep and close to major structures, image guidance is commonly used to improve target accuracy. The precise preparation and injection protocol can vary.
PRP does not replace cartilage on demand and should not be described as a guaranteed joint-regeneration procedure. The more defensible goal is improvement in pain and function for an appropriate candidate. A response can reduce limitations and support rehabilitation even when an x-ray remains unchanged.
The biologic rationale involves platelet-derived signals that may influence inflammation and tissue response. Human studies show promising symptom changes, but results vary, and the evidence base is smaller and less standardized than it is for some common treatments.
What the evidence suggests
Randomized and comparative studies have reported improvement after hip PRP, and some have compared it with hyaluronic acid or other injection approaches. However, studies use different PRP products, numbers of injections, patient groups, and outcome measures. That makes a single universal success rate misleading.
Evidence should be interpreted by severity and clinical context. A younger active adult with mild-to-moderate osteoarthritis and preserved strength is not identical to a patient with severe joint-space loss, major motion restriction, and constant night pain. Both deserve an honest discussion about likely benefit and alternatives.
The practical takeaway is that PRP may be reasonable for selected patients who understand uncertainty, have a joint-confirmed pain pattern, and are prepared to complete rehabilitation. It should not delay necessary surgical evaluation when symptoms or imaging indicate that joint replacement is the more appropriate pathway.
Who may be a candidate
Potential candidates often have symptomatic mild-to-moderate hip osteoarthritis, have tried appropriate conservative measures, and want to explore a nonsurgical option. They should be able to follow post-procedure instructions and participate in progressive strengthening and mobility work.
A patient’s candidacy also depends on medication, bleeding risk, active infection, systemic illness, and other medical factors. The clinician must review the full medication and supplement list. Anticoagulants and antiplatelet drugs must never be stopped without direction from the prescribing clinician.
PRP may be less predictable when arthritis is advanced, the joint has major structural deformity, or pain arises predominantly outside the joint. In those situations, another injection target, a different treatment, or orthopedic consultation may be more useful.
Procedure and recovery
The visit generally includes blood collection, processing, skin preparation, and image-guided injection. Patients should receive written instructions about medication, activity, transportation, and warning signs. Temporary post-injection soreness may occur.
Recovery usually moves from brief protection to gentle motion and then to progressive hip and trunk strengthening. Walking, stairs, cycling, lifting, and sport are restored according to symptoms and the clinician’s plan. An immediate return to maximal activity is not the goal.
Follow-up should compare the same functional markers over time: walking tolerance, sleep, range of motion, stair use, and desired activities. A decision to repeat treatment should be based on a meaningful prior response and clinical review, not on a predetermined package.
Can the Wolverine Peptide Stack support recovery after hip PRP?
For selected patients, Dr. Sobo may discuss pairing hip PRP with a physician-supervised Wolverine Peptide Stack containing BPC-157 and TB-500. The intent is to support the overall tissue-recovery environment while the patient follows the hip-specific protection, mobility, and strengthening plan.
This is an adjunctive strategy—not a substitute for accurate diagnosis, image-guided treatment, rehabilitation, or surgical referral when arthritis is advanced. Peptide therapy should not be represented as regrowing hip cartilage or guaranteeing a stronger PRP response. Direct human evidence evaluating BPC-157 and TB-500 specifically with hip PRP remains limited.
Patients can review Dr. Sobo’s Wolverine Peptide Stack in Stamford, CT and his article explaining how BPC-157 and TB-500 may fit into a recovery-focused regenerative plan.
Important: BPC-157 and TB-500 are not FDA-approved specifically for improving recovery after hip PRP. Any recommendation should follow an individualized review of medications, medical history, treatment goals, product sourcing, monitoring needs, and the patient’s complete rehabilitation plan.
Risks, alternatives, and next steps
PRP uses the patient’s own blood, but that does not make the procedure risk-free. Possible problems include temporary pain, bleeding, infection, injury to nearby structures, and lack of benefit. Image guidance and sterile technique are important safeguards.
Alternatives include structured physical therapy, weight management when relevant, analgesic strategies, activity modification, other injections, and surgery. The best choice depends on the diagnosis, severity, goals, and tolerance for recovery time.
Dr. Sobo provides individualized regenerative medicine evaluations at Optimal Health Medical. Explore platelet-rich plasma treatment and schedule a consultation to discuss whether PRP for hip osteoarthritis fits your medical picture.
How hip arthritis is diagnosed
The evaluation starts with the location and pattern of symptoms. True intra-articular hip pain often presents in the groin or front of the thigh, but patterns overlap. The clinician checks walking, hip rotation, strength, and movements that reproduce symptoms. Lower-back and neurologic screening may identify a different source.
Weight-bearing x-rays can show joint-space narrowing, bone spurs, or other changes. MRI is not required for every patient, but it may help when the diagnosis is uncertain or another structure is suspected. The severity shown on imaging must be interpreted alongside function and goals.
A diagnostic injection is sometimes considered when the pain source remains unclear. The point of this process is to reduce the chance of treating an image finding that is not actually responsible for the patient’s limitation.
PRP compared with common alternatives
Physical therapy addresses strength, mobility, balance, and movement strategy. It is often foundational whether or not an injection is chosen. Medication can reduce symptoms but must be selected around gastrointestinal, kidney, cardiovascular, and other risks.
Corticosteroid injections may provide shorter-term relief for some patients, while repeated exposure has tradeoffs that should be discussed. Hyaluronic acid is another injection approach, though recommendations and coverage vary. PRP has a different biologic rationale and cost profile and is frequently self-pay.
Hip replacement is not a failure of conservative care. For advanced arthritis with severe pain and loss of function, it can be the treatment most likely to restore quality of life. A regenerative treatment should not be used to indefinitely postpone an indicated surgical consultation.
Rehabilitation goals after hip PRP
Early exercises may focus on comfortable range of motion, walking mechanics, and gentle activation. Later phases build the gluteal muscles, trunk, and leg strength needed for stairs, standing, balance, and sport. Exercise dosage should increase without creating a prolonged flare.
Low-impact conditioning such as cycling, pool work, or an elliptical may help maintain fitness while impact is limited. The right choice depends on symptoms and access. Patients should not assume that all low-impact activity is automatically appropriate immediately after injection.
Return-to-activity criteria can include improved gait, tolerable range of motion, better single-leg control, strength symmetry, and the ability to complete a session without a significant next-day increase in symptoms.
Setting realistic expectations
The most realistic goal is a meaningful improvement in pain and daily function, not a promise of a new joint. Some patients may delay more invasive treatment; others may experience little change. The uncertainty should be discussed before payment and procedure.
Age alone does not determine success. Arthritis severity, body composition, metabolic health, activity demands, strength, sleep, and other pain conditions can all influence the experience. A younger patient can have advanced disease, and an older patient can remain highly functional with moderate changes.
A good consultation ends with a decision even when the decision is not PRP. The patient should understand the diagnosis, alternatives, expected timeline, warning signs, and the next review point.
Key takeaways
- Begin with an accurate diagnosis and a clearly defined goal.
- Use evidence and risk information for the exact therapy—not the category name alone.
- Track function, symptoms, side effects, and relevant objective measures.
- Coordinate treatment through a qualified clinician and keep follow-up appointments.
- Seek prompt care for severe or rapidly worsening symptoms.
Frequently asked questions
Does PRP work for hip osteoarthritis?
Research suggests some selected patients improve in pain and function, but results vary and PRP is not a guaranteed cure.
Can PRP regrow hip cartilage?
PRP should not be promised to regrow cartilage. The clinical goal is usually symptom and function improvement.
How is PRP injected into the hip?
Because the hip joint is deep, clinicians commonly use ultrasound or another imaging method to guide placement.
How long is recovery?
Patients often have a short protection period followed by gradual movement and strengthening. Full assessment may take weeks to months.
Is PRP better than a cortisone injection?
The treatments have different goals, timelines, and evidence. The best choice depends on the diagnosis and patient factors.
When is surgery a better option?
Advanced structural disease, severe functional loss, or failure of conservative care may make orthopedic surgical evaluation more appropriate.
Can the Wolverine Stack be used after hip PRP?
It may be considered as a physician-supervised adjunct for selected patients, but it does not regrow cartilage or guarantee a better PRP result. Direct evidence for the combination is limited, and timing, risks, and monitoring must be individualized.
Sources
- Randomized trial: PRP in hip osteoarthritis
- Randomized study: PRP versus hyaluronic acid for hip OA
- AAOS OrthoInfo: Osteoarthritis of the Hip
- Dr. Sobo: Wolverine Peptide Stack in Stamford, CT
- Dr. Sobo: Wolverine Peptide Stack—BPC-157 + TB-500 for Recovery
- FDA: July 23–24, 2026 Pharmacy Compounding Advisory Committee meeting materials
- FDA: Compounding and the FDA—Questions and Answers

Medically reviewed by